 Nix McRetro

Ahhhhh yes, now where was I? I’ve corrected my spiralling debt thanks to an early release of superannuation due to financial hardship. Taking away from future me isn’t too bad - especially as future me shouldn’t really exist. The fact that present day me exists is surprising to… me. For now I’m past that.

I’ve hit a bit of a problem with the ever-fast-approaching start of university. I can’t handle groups of people. Groups of people I don’t know anyway.

I have trialled visiting a gender therapy group repeatedly and either break down and fail to leave or get to the group, enter the building and… panic. I then escape the situation. Fear extinction will be difficult to achieve - especially in such a short time before university starts.

Doing nothing now will likely result in me deferring until 2025. In an effort to mitigate this I tried to restart antidepressants. I picked out the least side effect riddled one. In my case, that would be duloxetine (Cymbalta), an SNRI.

And no. I can’t even. Unrelenting bruxism 24/7. At the lowest dose. Every damn time. Bruxism is a known side effect of serotonergic antidepressants, but that still doesn’t tell me why I’ve had such a rough time with them. Great. So where to from here?

My anxiety seems to fuel my depression and seems to be specific to interacting with groups of people. Of course there are the drugs that no one wants to prescribe because they are bad for you. Mainly drugs in the barbiturate and benzodiazepine-classes. I would argue that killing myself is also bad for me. I would rather feel better some of the time than none of the time. They are not available to me, so…

I’m trialling bupropion (Zyban, Wellbutrin), a norepinephrine-dopamine reuptake inhibitor (NDRI). Little direct effect on serotonin, and no bruxism for me. It might help my anxious depression, although pooled trials found a modest advantage for SSRIs when anxiety was high. For the first two weeks everything felt magical and stimulating. My little honeymoon period. I was waiting for receptor down-regulation, though I couldn’t tell whether receptors explained any of that. Now I wait and see whether the benefit lasts.
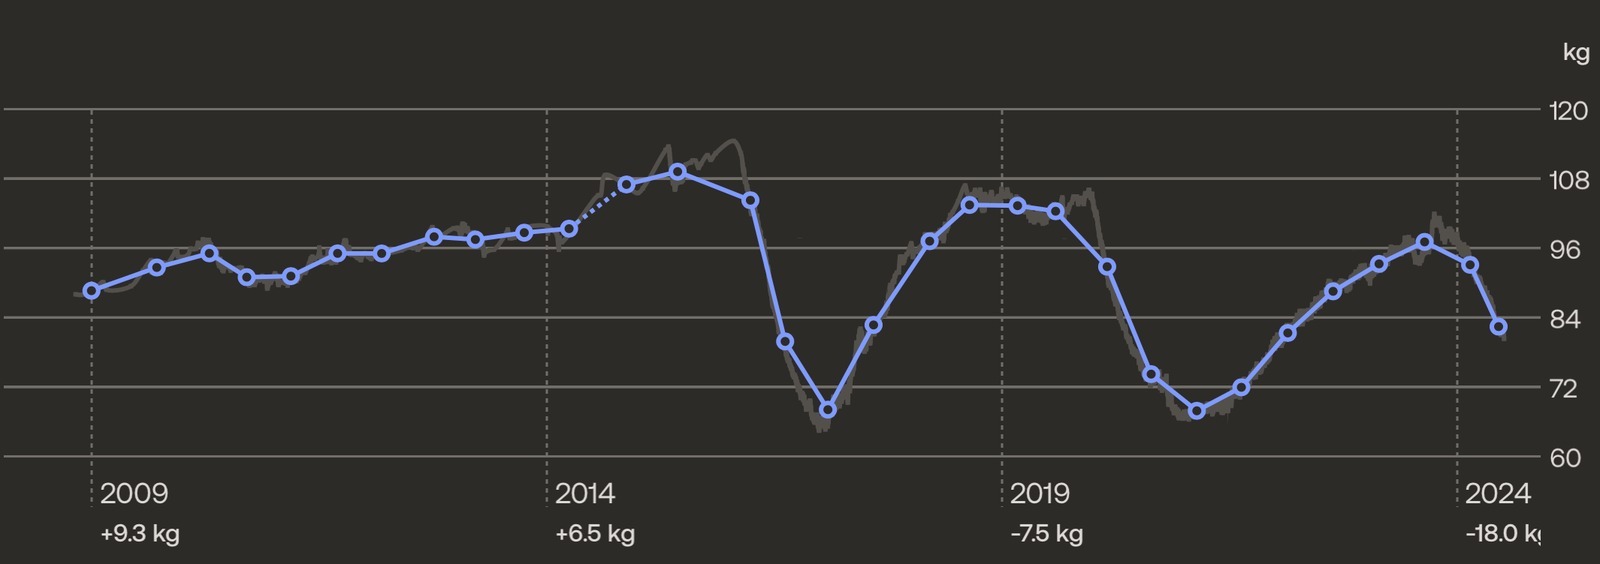
In other news I’ve scraped the top end of the so-called healthy BMI range. BMI isn’t the absolute best measure of health, but going from 34.8 to 24.8 was a pretty substantial change in my weight. I was also thinking about cycling my weight to see whether GAHT changed where I regained fat. Would it help with redistribution? I didn’t know whether that would work.
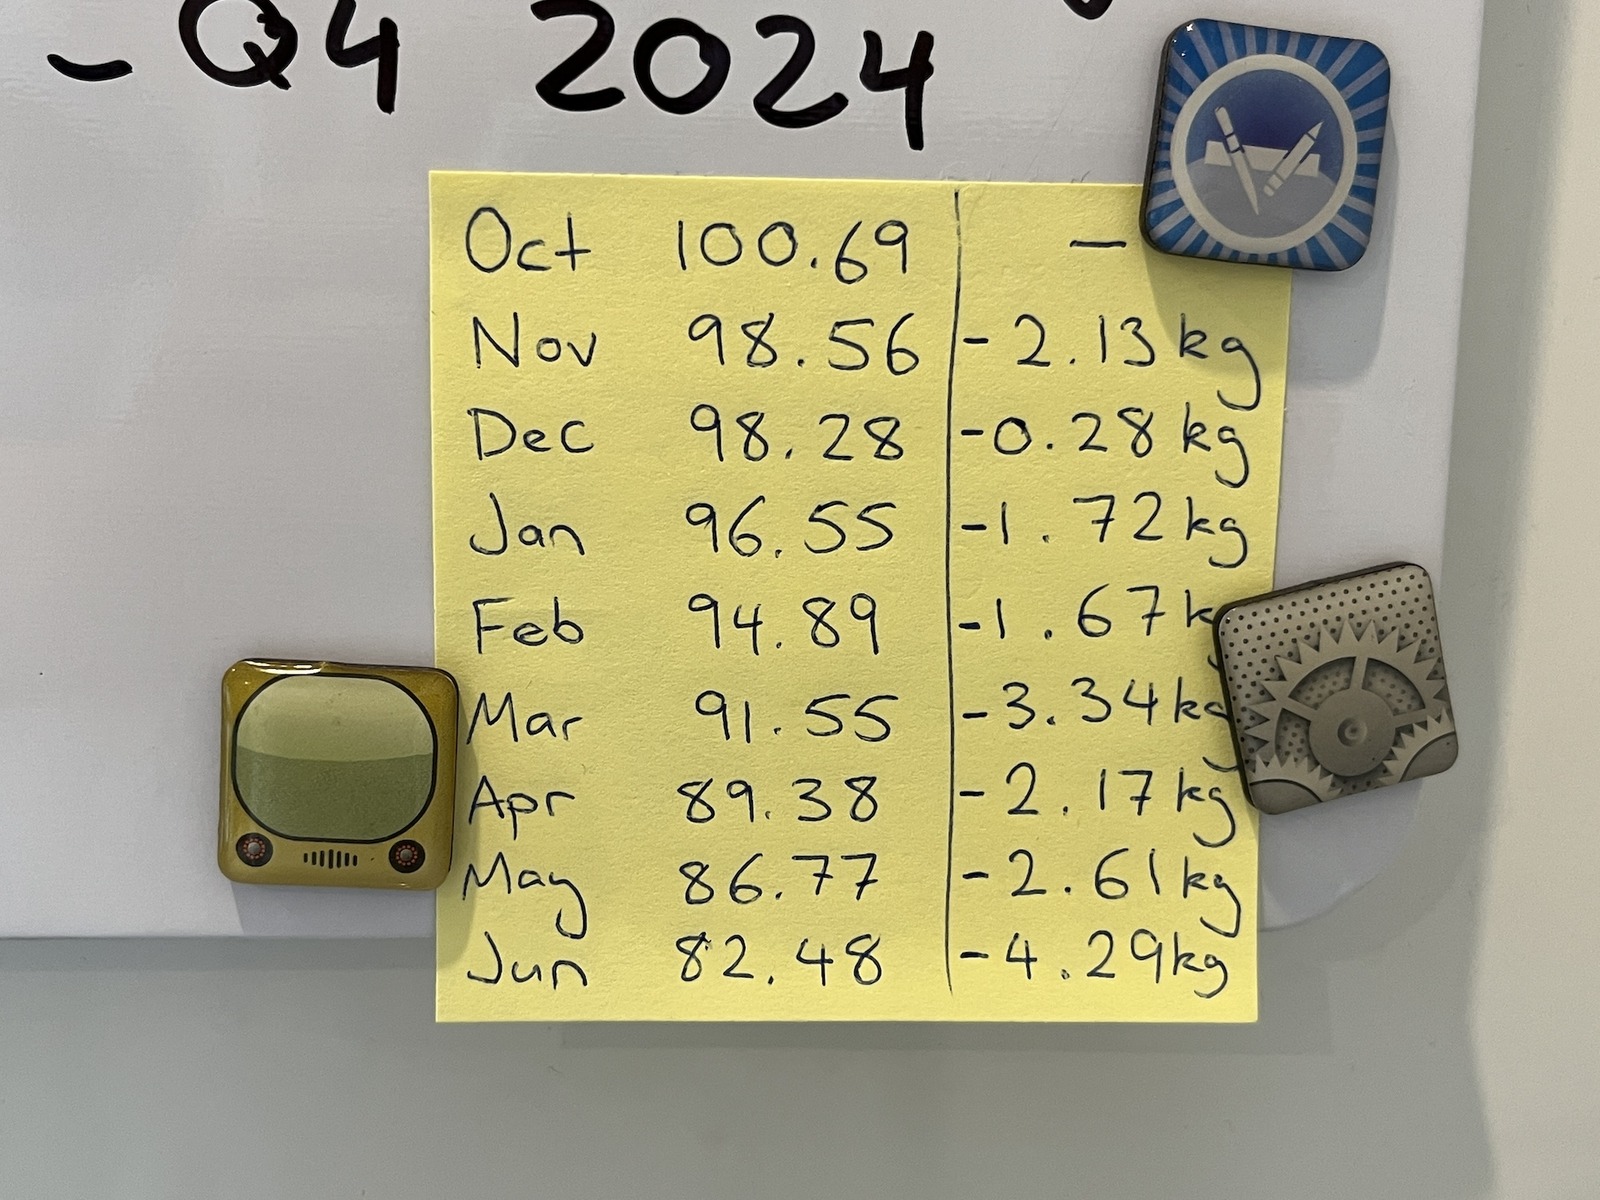
What an excellent segue into the medication side of things for being a transgender woman. I’ve been monitoring a few things over the past month or so.

Progesterone is expensive and I am poor. So I had been comparing compounded progesterone with commercial Prometrium. At 400mg/day split twice daily and measured in the trough, the compounded version gave me slightly higher numbers on one set of tests. Nice on paper, but that couldn’t tell me whether the products were equivalent. Food, formulation and release characteristics can all change what gets absorbed and when.
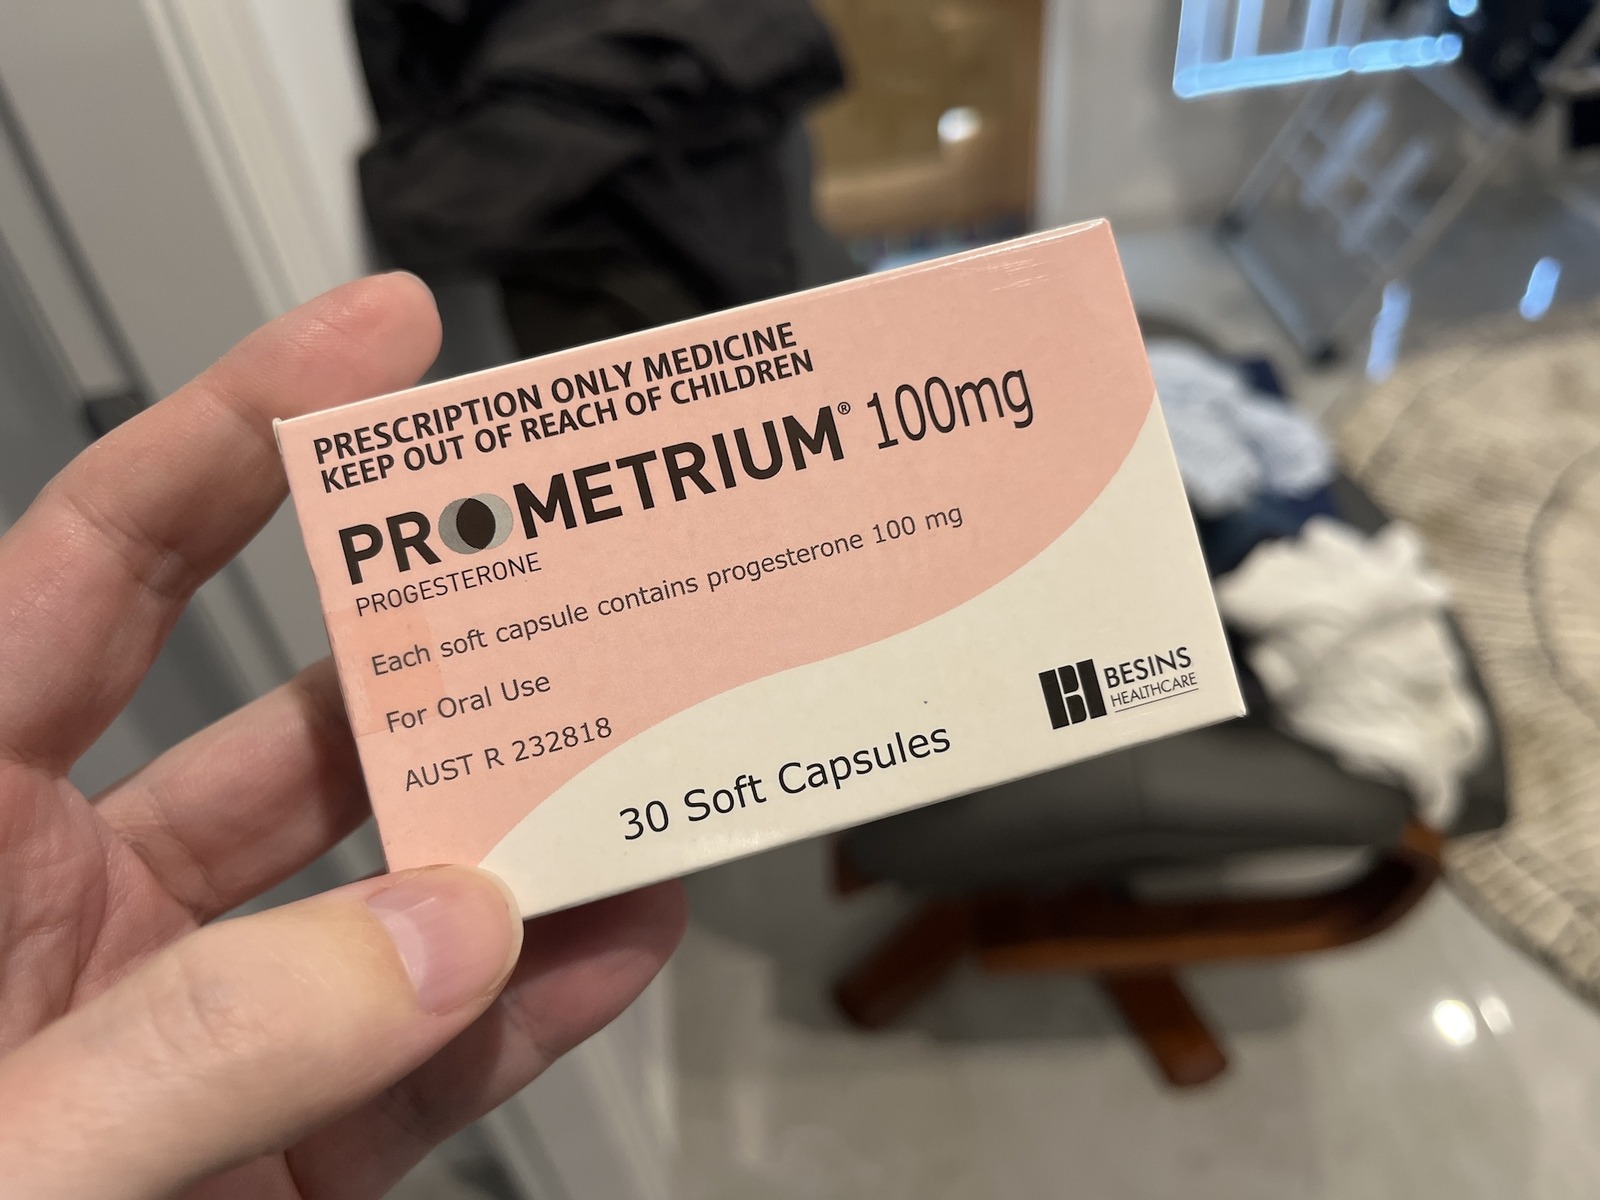
However, there was one unexpected effect I appreciated. When I took oil-based Prometrium 200mg with food, I got a short-lived sedated, mildly euphoric feeling that reminded me of 4-5mg of diazepam. The food part matters: it increases absorption, and the Prometrium leaflet says not to take it with food. I also noticed the effect after stopping finasteride. My best guess involved progesterone-derived neurosteroids such as allopregnanolone, though I hadn’t measured those.

For a few hours each day, at a big hit to my wallet, I can leave my anxiety behind and actually get things done. It’s a very desirable side effect for me. For now I am not taking any progesterone to retest my baseline - it should be very low but not quite zero.

One of the reasons for retesting my baseline was a pretty big confounding factor: I was now taking modified-release compounded progesterone. Comparing that with immediate-release Prometrium was getting messy. Over one week I increased the modified-release dose to 800mg/day to see whether anything changed. Nothing. No positive mental effects, no negative ones either. That was a very high dose, and any further dose experiments needed to go through my prescriber. It still didn’t tell me whether the formulations were equivalent.

I’m also checking serum DHT. That can tell me about what’s circulating, though it won’t tell me exactly what’s happening inside a hair follicle. I was mainly looking for shifts in steroid precursors on progesterone versus off progesterone. I’ll do another post when I have additional data.

It was also neat to see what my estradiol levels were soon after another set of pellets was implanted. I scored just over 1500pmol/L at about one week, compared with roughly 700pmol/L before the newest implants, and around 1200pmol/L another three weeks later. I’d called anything above 400pmol/L “gravy”, but more isn’t automatically better. The Australian guidance I was using targeted roughly 250 to 600pmol/L, adjusted to clinical response, so those early post-implant levels were above that range.

See what the bupropion made me do? This post is massive. Oh well, until next time! 🥰
Sources
- Efficacy of bupropion and the selective serotonin reuptake inhibitors in the treatment of major depressive disorder with high levels of anxiety (anxious depression): a pooled analysis of 10 studies
- Prometrium 100 and 200 mg - Consumer Medicine Information, published by MIMS May 2022
- A position statement on the hormonal management of adult transgender and gender diverse individuals
- Standards of Care for the Health of Transgender and Gender Diverse People, Version 8